

Cloud
Hospital
Institution PACS
The one already in use
Cloud
AIRead-CXR
Runs in the cloud
- Available to
- Institutions of any size
- Regions
- Deployed in your region on major cloud providers
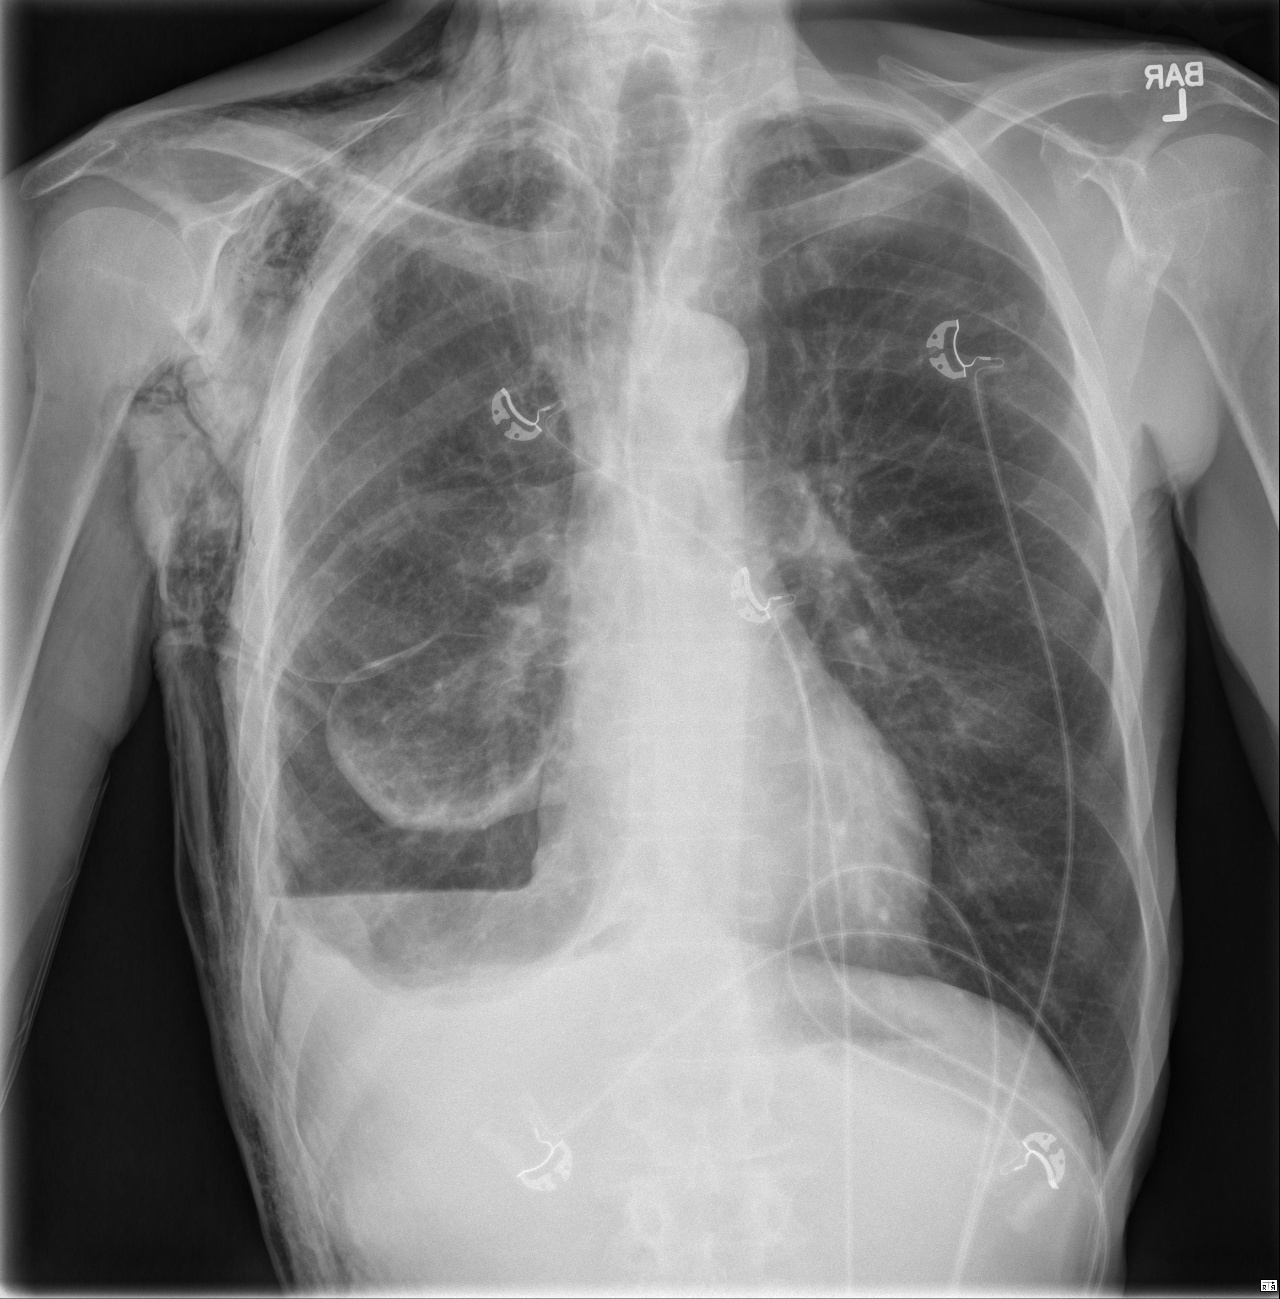
A 24-hour reading assistant for radiologists.Draft chest X-ray reports wait in your PACS reporting window.
Key figures
14M
Chest X-ray studies trained
Images + reports
84.5%
Clinical acceptability
Rated by thoracic radiologists · 478 ED patients · vs 4 imaging VLMs
AI Assistant
Your PACS as it is. Less report writing.
Image
Chest PA / AP
AI analysis
Medical Imaging VLM
Reporting software
Reporting pane
Storage
PACS
The one already in use
Image
Chest PA / AP
AI analysis
Medical Imaging VLM
Storage
PACS
The one already in use
Reporting software
Reporting pane
57+clinically validated findings
16Lung Parenchyma
6Pleural
3Infection & TB
6Cardiac & Vascular
5Mediastinal
6Bone & Fracture
11Medical Devices
4+Also covered
MFDS Approved · Adult (19+) PA and AP chest radiographs. Radiologists review, edit and sign off each draft.
Product information · Manual & Version(opens in a new tab)Compare with priorComing soon
Prior chest X-rays and reports are read alongside the current study, so follow-up drafts reflect the patient’s course.
FULL DEMO
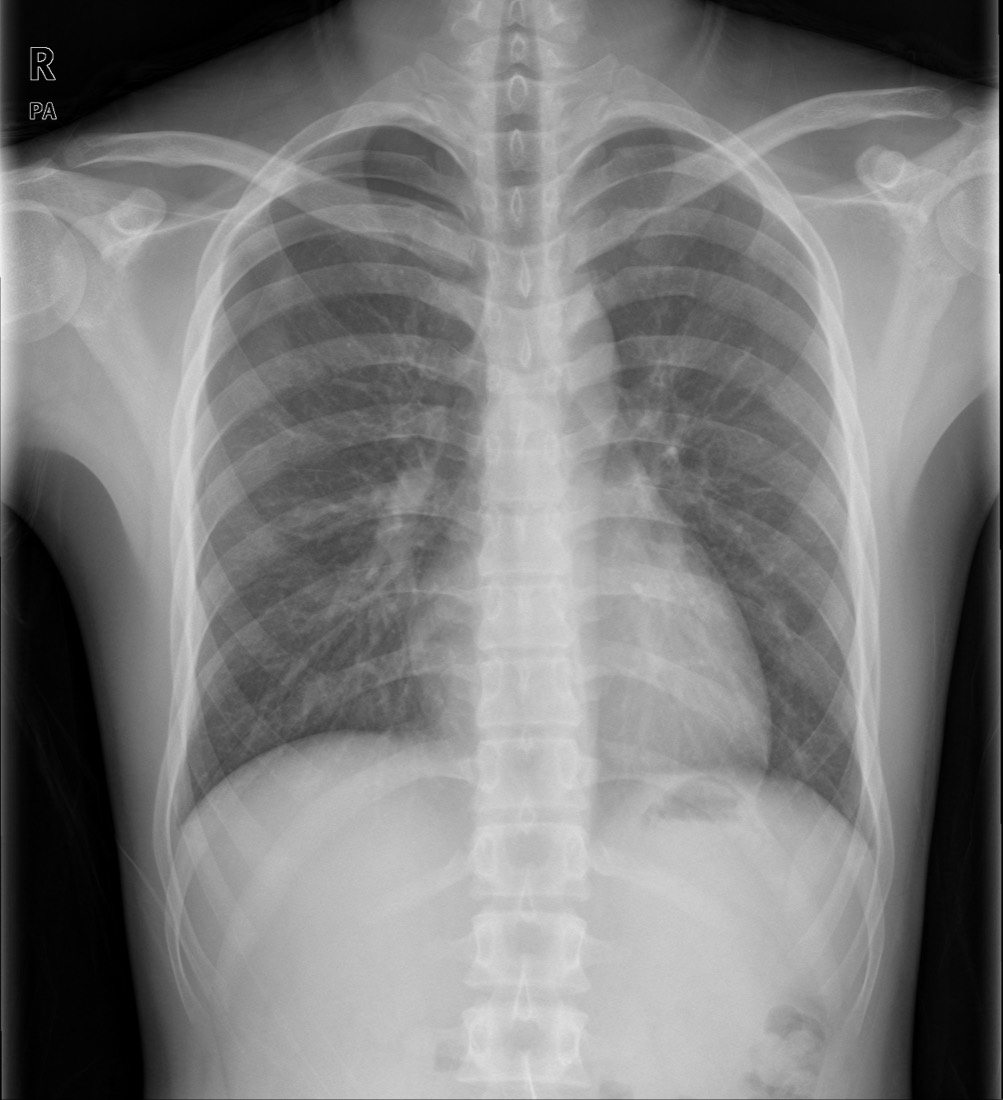
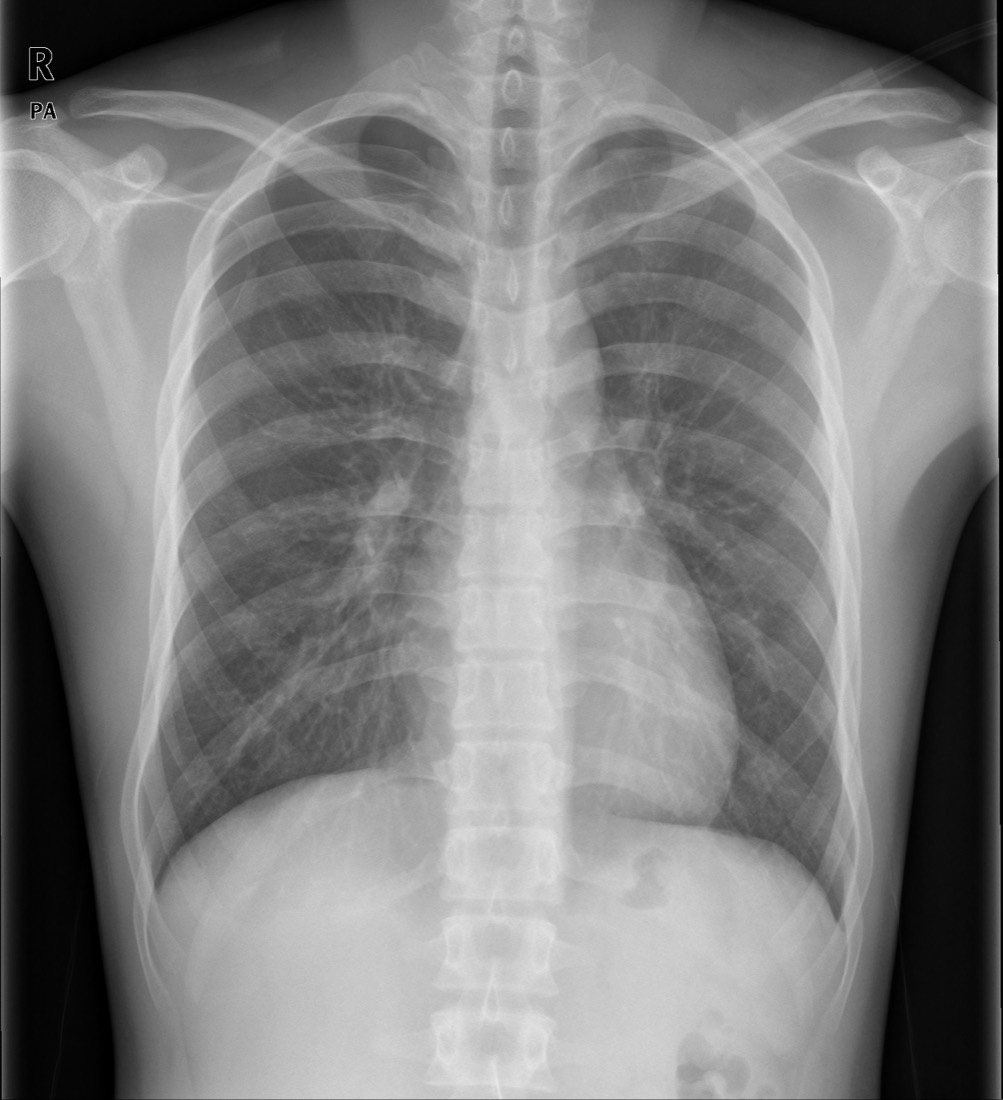
Demo screen · names and times are illustrative
STYLE
The same preliminary findings, written in the format and wording each hospital uses.
FINDINGS
Lungs
No focal airspace opacity.
Pleura
Small right apical pneumothorax is not substantially changed.
Small left apical pneumothorax, newly apparent.
No pleural effusion.
Cardiomediastinal contours
Normal heart size. No mediastinal shift.
Bones
No acute osseous abnormality identified.
Lines and Tubes
No indwelling thoracic device.
Others
No evident soft tissue abnormality.
IMPRESSION
1. Small bilateral apical pneumothoraces: right not substantially changed; left probably new. No tension features.
Integration
Integrated with



Using a different PACS?
We integrate with the PACS you already use.
Published evidence
Among five medical-imaging VLMs compared under the same conditions, including MedGemma, MAIRA-2, MedVersa, and Lingshu, AIRead-CXR had the highest clinical acceptability and the lowest clinically significant disagreement and hallucination rates.
AcceptabilityHigher is better
Disagreement (RADPEER 3b)Lower is better
Hallucination rateLower is better
AIRead-CXR
84.5%
5.3%
0.3%
Lingshu
41.1%
43.0%
11.0%
MAIRA-2
65.6%
24.5%
17.4%
MedGemma
71.4%
16.8%
5.4%
MedVersa
63.7%
25.9%
12.3%
Reference: radiologist reports
74.3%
13.9%
0.1%
| Evaluated | Clinical acceptabilityHigher is better | Significant disagreement (RADPEER 3b)Lower is better | Hallucination rateLower is better |
|---|---|---|---|
| AIRead-CXR | 84.5% | 5.3% | 0.3% |
| Lingshu | 41.1% | 43.0% | 11.0% |
| MAIRA-2 | 65.6% | 24.5% | 17.4% |
| MedGemma | 71.4% | 16.8% | 5.4% |
| MedVersa | 63.7% | 25.9% | 12.3% |
| Reference: radiologist reports | 74.3% | 13.9% | 0.1% |
Reported as AIRead in the paper
Study design: 478 ED patients, same-day CT reference.

IF 17.6 · 3 papers

IF 7.4 · 2 papers
IF 6.0 · 1 paper
Based on 2025 Journal Citation Reports
Deployment
Hospital
Institution PACS
The one already in use
Cloud
AIRead-CXR
Runs in the cloud
Hospital
Data stays on site
Institution PACS
The one already in use
AIRead-CXR server
Installed and runs on site
Review the PACS, study volume, and network environment.
Review preliminary report quality in the real reading environment.
Configure cloud or on-premise deployment and connect the PACS.
Provide user training, monitoring, and regular updates.
Next step
Considering AIRead-CXR for your institution? Tell us about your reading environment and requirements.